


In vitro susceptibility of Borrelia afzelii, the causative agent of Lyme borreliosis, to the supernatants of Lactiplantibacillus plantarum and Saccharomyces boulardii
- University of Belgrade, Institute for Medical Research, National Institute of the Republic of Serbia, Centre of Excellence for Food and Vector-Borne Zoonoses, Group for Medical Entomology, Belgrade, Serbia
- University of Belgrade, Vinča – Institute for Nuclear Sciences, National Institute of the Republic of Serbia, Department of Molecular Biology and Endocrinology, Belgrade, Serbia
- University of Belgrade, Faculty of Pharmacy, Department of Microbiology and Immunology, Belgrade, Serbia
- University of Belgrade, Faculty of Biology, Department of Microbiology, Belgrade, Serbia
ABSTRACT
Introduction: Lyme borreliosis (LB) is a multisystem disorder caused by bacteria of the Borrelia burgdorferi sensu lato complex, transmitted to humans through the bite of Ixodes spp. ticks. Standard treatment typically involves prolonged antibiotic therapy. Currently, no topical product is available on the market for prophylactic use following a tick bite.
Aim: The aim of the study was to investigate in vitro the effects of supernatants derived from the probiotic microorganisms Saccharomyces boulardii and Lactiplantibacillus plantarum, and their mixtures, on the growth and motility of Borrelia afzelii.
Materials and methods: To test the susceptibility of B. afzelii to probiotic microorganisms, a modified broth microdilution method adapted for Borrelia species was employed. Minimum inhibitory concentrations (MICs) were determined by evaluating both the number and motility of B. afzelii after 72 hours of incubation with supernatants under anaerobic conditions, compared to a positive control consisting of untreated B. afzelii culture.
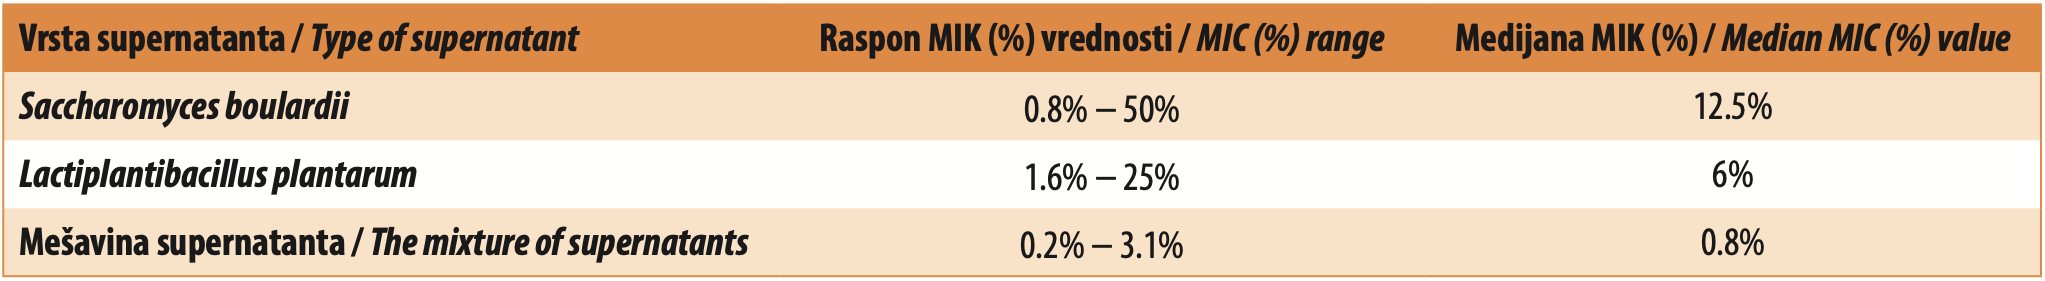
Results: The MIC was defined as the lowest concentration of the tested supernatant at which borrelia were non-motile and their number was reduced compared to the positive control. The following median MIC values were determined: 12.5% for S. boulardii, 6% for L. plantarum, and the lowest median MIC value of 0.8% was defined for the supernatant mixture of probiotic microorganisms.
Conclusion: The mixture of S. boulardii and Lactiplantibacillus plantarum exhibited the strongest inhibitory effect on the growth and motility of B. afzelii. These results provide a foundation for further investigation into the molecular mechanisms of the inhibitory activity of probiotic microorganisms against Borrelia species.
INTRODUCTION
Lyme borreliosis (LB) is a zoonosis, the causative agents of which are transmitted through the bite of infected ticks of the genus Ixodes. The causative agents of LB are spiral-shaped bacteria from the Borrelia burgdorferi sensu lato (s.l.) complex [1],[2]. The primary vectors in Europe are ticks of the species Ixodes ricinus [3]. Since LB is a multisystemic disease affecting both humans and animals, it can present with various clinical manifestations, such as skin lesions, musculoskeletal, neurological, ocular, and/or cardiovascular symptoms. In some cases, the infection may be asymptomatic, while in later stages, LB can be misdiagnosed due to the complexity of its clinical signs and symptoms [2],[4].
The Borrelia burgdorferi sensu lato (s.l.) complex currently comprises 21 named Borrelia species. While in North America the primary causative agent of LB is Borrelia burgdorferi sensu stricto (s.s.), Europe exhibits greater Borrelia diversity, with five confirmed pathogenic species: Borrelia afzelii, Borrelia garinii, B. burgdorferi s.s., Borrelia spielmanii, and Borrelia bavariensis. In addition, Borrelia lusitaniae, Borrelia valaisiana, and Borrelia bissettii have also been isolated or detected in humans, although their pathogenic potential has not yet been fully elucidated [2].
While B. afzelii, B. garinii, and B. valaisiana are the most common Borrelia species found in ticks across most European countries [5], in Serbia the dominant species is B. lusitaniae, followed by B. afzelii, B. bavariensis, B. garinii, B. valaisiana, and B. burgdorferi s.s. [6],[7]. The most common clinical manifestation of Lyme disease in Serbia is erythema migrans, observed in 93.2% of cases, followed by neurological (2.8%), musculoskeletal (2.4%), and cardiac (1.1%) manifestations [8].
In general, the course of LB can be divided into three clinical stages. The first stage-early localized infection-most commonly presents as erythema migrans, a characteristic red skin lesion in the form of a concentric circle that appears at the site of the infected tick bite, typically around seven days after infection. This lesion may be accompanied by a range of symptoms, including fever, headache, muscle and joint pain, and swollen lymph nodes [1],[2],[9]. The second stage-early disseminated infection-develops several weeks to several months after the tick bite. If antibiotic therapy is not administered during the first stage, Borrelia from the primary skin lesion can disseminate throughout the body, potentially affecting the nervous system, skin, joints, and heart. The third stage-late disseminated infection-occurs several months or even years after the bite of an infected tick and can lead to severe neurological, rheumatological, and dermatological complications [1],[2]. Although all pathogenic Borrelia species can cause erythema migrans and disseminate into the circulation, B. afzelii most often remains localized to the skin and is commonly associated with late-stage skin manifestations, such as acrodermatitis chronica atrophicans (ACA), a condition found exclusively in Europe. Borrelia burgdorferi s.s. is primarily associated with rheumatological manifestations, particularly Lyme arthritis, which is more frequently observed in North America than in Europe. Borrelia garinii and B. bavariensis are most often linked to neurological symptoms, including Lyme neuroborreliosis, which may occur during the second and third stages of the disease [2].
Following diagnosis, the duration and dosage of antibiotic therapy, administered either orally or intravenously, are determined based on the stage of the disease, the patient’s age, and immune status. The most commonly used antibiotics include doxycycline, amoxicillin, ceftriaxone, cefuroxime, and azithromycin, typically prescribed for a period of 10 to 30 days, depending on the clinical form and stage of the disease [1]. The best protection against Lyme borreliosis (LB) is to avoid tick bites and to carefully examine the skin after spending time outdoors. Prophylactic antibiotic use following a tick bite is not recommended, as not every tick is infected with Borrelia, and not every bite from an infected tick results in transmission of the pathogen. Currently, there are no guidelines or recommendations for prophylactic antibiotic use after tick bites in Europe. To date, there is no topical product available on the market that can be applied to the skin after a tick bite to prevent the transmission of Borrelia. Similarly, no preparation exists for the local treatment of erythema migrans aimed at preventing further dissemination of Borrelia into the systemic circulation. Unlike pathogenic Borrelia species, which cause both local and systemic manifestations of LB requiring antibiotic therapy, probiotic microorganisms have demonstrated beneficial effects on human health [10],[11]. Certain strains produce antimicrobial substances, such as organic acids, bacteriocins, peptides, and polysaccharides, that are released into the culture supernatant during cultivation [12]. The probiotic yeast Saccharomyces boulardii has been shown in vitro to inhibit the growth of various pathogenic and opportunistic microorganisms, including Candida albicans, Escherichia coli, Salmonella enterica serovar Typhi, Shigella dysenteriae, Vibrio cholerae, and Salmonella enteritidis [12],[13]. Additionally, certain lactic acid bacteria, including Lactiplantibacillus plantarum, help prevent pathogen colonization by competing for nutrients and adhesion sites, altering environmental conditions to inhibit pathogen growth, producing antimicrobial compounds, and modulating the immune response [14],[15].
Bacterial evolution over time, combined with the widespread and increasing use of antibiotics globally, has significantly contributed to the rise of antimicrobial resistance, a major threat to public health worldwide. In 2019 alone, antimicrobial resistance was responsible for at least 1.27 million deaths globally, underscoring the serious risk it poses to human health across all age groups [16]. Due to the limitations in LB treatment, there is a need to develop safe and effective alternative approaches, such as a topical preparation based on biologically active components that can be applied prophylactically after a tick bite or at the site of the primary skin lesion. The goal is to prevent further dissemination of Borrelia infection and thereby significantly reduce or eliminate the need for antibiotic therapy.
The aim of this study was to investigate in vitro the growth, reproduction, and motility of B. afzelii in the presence of supernatants from S. boulardii, L. plantarum, and their mixtures, as well as to determine their minimum inhibitory concentration (MIC) values.
MATERIALS AND METHODS
The study tested the B. afzelii strain RS163_11i, previously isolated from I. ricinus ticks [6], and maintained within the isolate collection of the Institute for Medical Research, National Institute of the Republic of Serbia, University of Belgrade. The strain was preserved at −80 °C in Brucella-glycerol broth and subsequently recultivated in Barbour-Stoenner-Kelly H (BSK-H) medium (HiMedia, India). Cultivation was carried out at 33 °C until a Borrelia concentration of 1–2 × 10⁶ cells/ mL was achieved. Cell counts were determined using a Neubauer counting chamber (Brand GmbH & Co. KG, Wertheim, Germany) under dark-field microscopy [17].
To prepare the supernatants, lyophilized cultures from a commercially available probiotic formulation were used as the source for isolating pure cultures of S, boulardii and L, plantarum. These isolates were prepared at the Department of Microbiology and Immunology, Faculty of Pharmacy, University of Belgrade.
Two-fold serial dilutions of S. boulardii, L. plantarum, and their mixed supernatants were prepared in BSK-H medium. For each test, 100 µL of the undiluted supernatant (initial concentration 100%) or its dilution was mixed with 100 µL of the B. afzelii culture (1–2 × 10⁶ cells/mL). The B. afzelii culture without supernatant served as a positive control, while BSK-H medium without the addition of bacteria was used as a negative control. For each tested probiotic microorganism (S. boulardii, L. plantarum, and their mixtures), ten serial two-fold dilutions were prepared, ranging from 100% to 0.2% concentration. The mixed supernatant was prepared in a 1:1 ratio by combining 50 µL of each individual supernatant at corresponding dilution levels, starting from the maximum concentration of 100% for each strain.
Ceftriaxone was used as the reference antibiotic control in the broth microdilution method for Borrelia, and was tested at concentrations ranging from 8 to 0.016 μg/mL, as previously described [18]. The antimicrobial activity of the supernatants and the control antibiotic ceftriaxone was evaluated using a modified broth microdilution method adapted for Borrelia, as neither the European Committee on Antimicrobial Susceptibility Testing (EUCAST) nor the Clinical and Laboratory Standards Institute (CLSI) provide standardized guidelines or interpretive criteria for this method, including MIC breakpoints for Borrelia spp [17]. Briefly, the broth microdilution method for determining the MIC values of antibiotics and tested supernatants was performed using sterile 96-well microtiter plates. The first column served as a positive control containing Borrelia culture, while the second column served as a negative control with BSK-H medium. Wells in columns three through twelve were filled with mixtures of Borrelia culture and the tested substances at serially decreasing concentrations [17]. The tested concentration range of probiotic supernatants in the microtiter plates was 50% to 0.1% for individual strains, 25% to 0.05% for the mixed supernatants, and 168 μg/ mL to 0.3 μg/mL for the control antibiotic ceftriaxone [17]. Each experiment was performed in duplicate, with three technical replicates per condition. Following the setup of the microdilution assay, the microtiter plates were incubated for 72 hours at 33 °C in a GasPak™ EZ anaerobic container system (BD), equipped with an anaerobic generator and indicator. After incubation, MIC values were determined. Dark-field microscopy was used to assess Borrelia cell count and motility, and results were compared between samples treated with the tested supernatants, the positive control (untreated Borrelia culture), and the control antibiotic. MIC was defined as the lowest concentration of the tested probiotic supernatants (S. boulardii, L. plantarum, or their mixture) or antibiotics during co-cultivation with B. afzelii at which the Borrelia cells were either non-motile or showed significantly reduced motility, accompanied by a decrease in their number compared to the positive control.
STATISTICAL ANALYSIS
Statistical analysis was performed using the non-parametric Kruskal-Wallis and Mann-Whitney tests. Data were presented as median (minimum–maximum), and statistical significance was determined at a p-value threshold of 0.05.
The results are presented in tabular form. All data analyses were conducted using the R programming environment (R Core Team, 2024).
RESULTS
After 72 hours of incubation at 33 °C, MIC values were determined for S. boulardii, L. plantarum, their mixture, and the control antibiotic ceftriaxone. The Kruskal-Wallis test revealed a statistically significant difference among the MIC values of the tested supernatants (S. boulardii, L. plantarum, and their mixture) (p = 0.01). Wilcoxon test showed significant differences between the MIC of S. boulardii and the mixture (p = 0.02), as well as between L. plantarum and the mixture (p = 0.01). No statistically significant difference was observed between the MIC values of the supernatants of S. boulardii and L. plantarum (p = 0.68). Statistical analysis demonstrated that the mixture of the tested probiotic supernatants inhibited the growth and reproduction of B. afzelii more effectively than the individual supernatants alone.
The most effective supernatant in inhibiting the growth, reproduction, and motility of B. afzelii was the mixture of probiotic supernatants, with a median MIC value of 0.8%. The results are presented in Table 1.
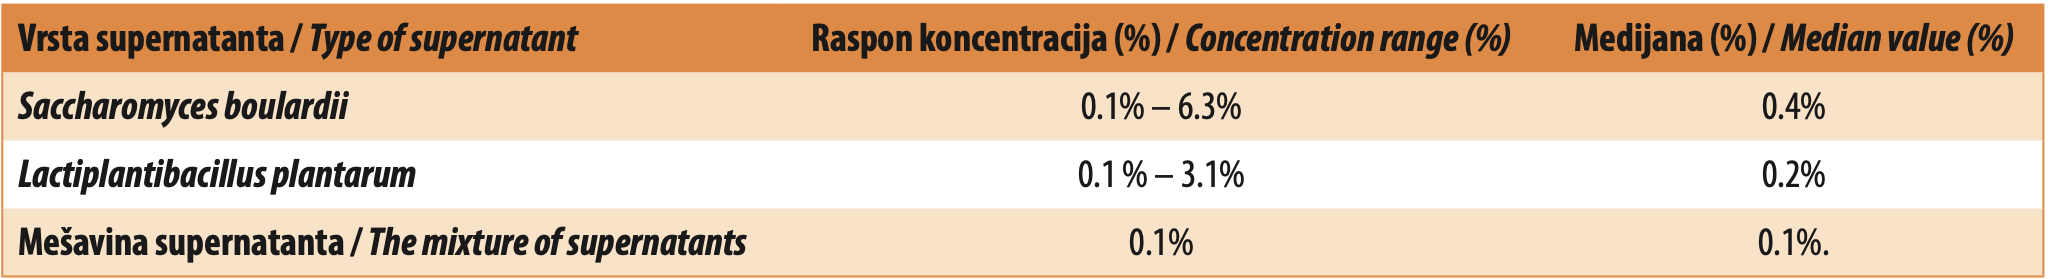
In addition to the defined MIC values for the supernatants of S. boulardii, L. plantarum, and their mixture, lower concentrations of these probiotic supernatants were associated with increased Borrelia motility and cell numbers compared to the positive control. The presence of supernatants from S. boulardii, L. plantarum, and their mixture stimulated both the number and motility of Borrelia compared to the positive control. Notably, B. afzelii exhibited the greatest increase in motility and abundance in the presence of the mixed supernatants at a median concentration of 0.1%. These results are presented in Table 2.
The MIC value of the tested control antibiotic for B. afzelii was 0.016 μg/mL (corresponding to 0.3 μg/mL in microtiter plates), consistent with previously published data and confirming its established inhibitory effect on the growth and reproduction of Borrelia.
DISCUSSION
Saccharomyces boulardii is the only eukaryotic microorganism used as a probiotic in the pharmaceutical industry. To date, two mechanisms of its action against pathogens have been identified: it binds to bacteria and their toxins, promoting their elimination, and it secretes specific proteins involved in the degradation of toxins and/or pathogenic cellular components [19]. A study by Rajkowska and Kunicka-Styczyńska [20] demonstrated that S. boulardii binds to enteropathogenic bacteria (E. coli, S. enterica serovar Typhimurium, Staphylococcus aureus, Campylobacter jejuni, and Enterococcus faecalis), thereby facilitating their elimination from the body. The study also showed that S. boulardii significantly reduces the number of Listeria monocytogenes, Pseudomonas aeruginosa, and S. aureus cells, and additionally slows the growth of L. monocytogenes and P. aeruginosa.
One of the key mechanisms by which L. plantarum and other lactic acid bacteria affect pathogens is the production of a range of antimicrobial compounds, including bacteriocins, hydrogen peroxide, organic acids, acetone, and fatty acids [21],[22]. Antimicrobial peptides known as bacteriocins exhibit bactericidal activity or inhibit the growth of related bacteria, including pathogenic strains. They possess several advantageous properties, notably their effectiveness against antibiotic-resistant pathogens and their low or negligible toxicity to eukaryotic cells [23]. For example, the bacteriocin plantaricin PLNC8 αβ, produced by L. plantarum, has demonstrated antimicrobial activity against the periodontal pathogen Porphyromonas gingivalis by inducing outer membrane deformation and cell lysis.
In light of the previously described antimicrobial properties of both probiotic microorganisms, the initial hypothesis suggested their potential antibacterial effect. The main objective of this study was to examine, for the first time, their inhibitory activity against Borrelia afzelii, the causative agent of LB, in vitro. However, comparisons with earlier studies are limited due to differences in methodology and the microbial strains tested. Additionally, this study provides the first preliminary results on Borrelia using the broth microdilution method, which had not previously been applied to the probiotic microorganisms in question. In a 2012 study, the antimicrobial potential of S. boulardii supernatant was evaluated against S. aureus, E. coli, C. albicans, and Aspergillus niger using the agar diffusion method [12]. Their results were expressed as zones of inhibition (in millimeters), which are not directly comparable to the findings of our study due to differences in methodology, the test organisms used, and the way results were reported-in our case, as percentages. The antimicrobial activity of L. plantarum supernatant was previously confirmed using the agar point diffusion method against E. coli, L. monocytogenes, E. faecalis, and P. aeruginosa, with the size of the inhibition zone serving as an indicator of antimicrobial intensity [24]. In the experiment where the broth microdilution method was used [23], as in our study, a series of two-fold dilutions of various types of plantaricins were tested. However, unlike that study, our research employed whole supernatants of probiotic microorganisms and B. afzelii from the B. burgdorferi s.l. complex, using a modified microdilution method. On the other hand, the broth microdilution method for Borrelia is not standardized; as previously mentioned, neither EUCAST nor CLSI provides guidelines for performing this method on Borrelia, including antibiotic susceptibility testing. It is important to note that MIC breakpoint values for antibiotics have not been established for bacteria within the B. burgdorferi s.l. complex. Alongside the MIC values we determined for the tested probiotic microorganisms, a significant part of our results includes percentage data indicating a stimulatory effect on the number and motility of Borrelia. These findings represent an initial step toward understanding how specific probiotic strains may influence the growth and behavior of Borrelia under controlled, in vitro conditions. This opens up the possibility for further optimization of the BSK-H medium (Hi-Media), the standard substrate for Borrelia cultivation, with the goal of enhancing its efficiency for isolating and growing Borrelia from various biological samples. While the Sigma BSK-H medium is expensive, Hi-Media offers a more affordable alternative with the same composition, potentially reducing testing expenses significantly. The effectiveness of the medium is critical, as successful isolation and cultivation of Borrelia depend heavily on its quality. In this regard, previous research, such as the study by Ružić-Sabljić et al. [25], demonstrated that the Hi-Media medium more effectively promotes the growth of Borrelia. Our research further supports these findings by demonstrating that the addition of probiotic supernatants to Borrelia enhances their growth and motility, thus opening new possibilities for using probiotics to optimize laboratory cultivation conditions. Moreover, the MIC values obtained for the supernatants of S. boulardii, L. plantarum, and their mixture against B. afzelii (Table 1) represent the first such data reported for Borrelia. These results provide a foundation for future studies on the inhibitory effects of probiotic supernatants on the growth, reproduction, and motility of Borrelia.
Considering the potential significance of the obtained MIC results for probiotic microorganisms and future research directions, additional aspects warrant attention-specifically, the development of a topical (prophylactic) formulation to be applied after a tick bite, aimed at preventing the need for oral and/or intravenous antibiotic treatment. Currently, no topical or prophylactic drug for LB exists. However, in 2017, a pilot clinical study investigated the topical application of a 10% azithromycin gel following tick bites [26]. The results were unsatisfactory, and the study did not support recommending azithromycin gel for prophylactic use. Another study explored a similar approach, providing evidence for the effectiveness of topical azithromycin cream in preventing LB However, this protective effect, achieving 100% prevention of infection after a tick bite, has so far only been demonstrated in mice [27].
All of this highlights the need to develop a topical preparation with a different formulation and mechanism of action. In this context, the prospect of replacing antibiotics with natural products, which do not cause side effects and pose a lower risk of promoting antimicrobial resistance, becomes increasingly relevant. Developing a topical probiotic formulation based on the tested probiotic microorganisms could play a significant role in preventing erythema migrans and potentially inhibiting the systemic spread of Borrelia. Our research demonstrated that at certain concentrations, probiotic microorganism supernatants reduce the number and motility of Borrelia, although the underlying molecular mechanisms were not investigated. Therefore, future studies should focus on identifying the active components within these supernatants and elucidating the molecular pathways through which the whole supernatants and/or their components inhibit the growth and motility of B. afzelii, the causative agent of LB. This highlights a promising area for further research aimed at developing a topical probiotic preventive formulation based on the tested probiotic strains.
CONCLUSION
This study demonstrated that the supernatants of S. boulardii and L. plantarum exhibit antimicrobial activity against B. afzelii. The mixed supernatants of these two probiotic microorganisms showed the strongest effect, with a median MIC value of 0.8%, highlighting their potential for further investigation. Interestingly, at lower concentrations, specifically around a median of 0.1%, the supernatants and their mixture stimulated Borrelia growth and increased motility, indicating the need for additional research to better understand these effects. Potential directions for future research include analyzing the composition of the supernatants and investigating the molecular mechanisms underlying the inhibition of B. afzelii growth, reproduction, and motility. Such studies would primarily pave the way for developing a topical prophylactic preparation to be applied after a tick bite, aimed at preventing the onset of erythema migrans. This approach could help reduce the systemic dissemination of Borrelia, lower the risk of LB-related complications, and minimize the reliance on antibiotics.
Informations

-
Keywords:
-
Received:
-
Revised:
-
Accepted:
-
Online first:
-
DOI:
-
Cite this article:

Gorana Veinović
Group for Medical Entomology, Centre of Excellence for Food and Vector-Borne Zoonoses, Institute for Medical Research, University of Belgrade
4 Dr Subotića Street, 11129 Belgrade, Serbia
E-mail:
1. Stanek G, Strle F. Lyme borreliosis – from tick bite to diagnosis and treatment. FEMS Microbiol Rev. 2018;42(3):233-58. doi: 10.1093/femsre/fux047. [CROSSREF]
2. Stanek G, Wormser GP, Gray J, Strle F. Lyme borreliosis. The Lancet. 2012 Feb;379(9814):461-73. doi: 10.1016/s0140-6736(11)60103-7. [CROSSREF]
3. Sykes RA, Makiello P. An estimate of Lyme borreliosis incidence in Western Europe. J Public Health. 2016 Mar 9;fdw017. doi: 10.1093/pubmed/fdw017. [CROSSREF]
4. Geebelen L, Lernout T, Devleesschauwer B, Kabamba-Mukadi B, Saegeman V, Belkhir L, et al. Non-specific symptoms and post-treatment Lyme disease syndrome in patients with Lyme borreliosis: a prospective cohort study in Belgium (2016–2020). BMC Infect Dis. 2022 Sep 28;22(1):756. doi: 10.1186/ s12879-022-07686-8. [CROSSREF]
5. Estrada-Peña A, Cutler S, Potkonjak A, Vassier-Tussaut M, Van Bortel W, Zeller H, et al. An updated meta-analysis of the distribution and prevalence of Borrelia burgdorferi s.l. in ticks in Europe. Int J Health Geogr. 2018 Dec;17(1):41. doi: 10.1186/s12942-018-0163-7. [CROSSREF]
6. Ćakić S, Veinović G, Cerar T, Mihaljica D, Sukara R, Ružić‐Sabljić E, et al. Diversity of Lyme borreliosis spirochetes isolated from ticks in Serbia. Med Vet Entomol. 2019 Dec;33(4):512-20. doi: 10.1111/mve.12392. [CROSSREF]
7. Milutinović M, Masuzawa T, Tomanović S, Radulović Ž, Fukui T, Okamoto Y. Borrelia burgdorferi sensu lato, Anaplasma phagocytophilum, Francisella tularensis and their co-infections in host-seeking Ixodes ricinus ticks collected in Serbia. Exp Appl Acarol. 2008 Aug;45(3–4):171-83. doi: 10.1007/s10493-008-9166-6. [CROSSREF]
8. Mladenović J. Epidemiološki Aspekti Lajmske Bolesti na Teritorije Građa Beograda. Medicinski fakultet, Univerziteta u Nišu; 2014.
9. Steere AC, Strle F, Wormser GP, Hu LT, Branda JA, Hovius JWR, et al. Lyme borreliosis. Nat Rev Dis Primer. 2016 Dec 15;2(1):16090. doi: 10.1038/ nrdp.2016.90. [CROSSREF]
10. Cohrssen A. KB. Probiotics [Internet]. American Family Physician; 2008. Available from: https://www.aafp.org/pubs/afp/issues/2008/1101/p1073.html. [HTTP]
11. Garcia-Gonzalez N, Battista N, Prete R, Corsetti A. Health-Promoting Role of Lactiplantibacillus plantarum Isolated from Fermented Foods. Microorganisms. 2021 Feb 10;9(2):349. doi: 10.3390/microorganisms9020349. [CROSSREF]
12. Ali MAE, Abdel-Fatah OM, Janson JC, Elshafei AM. Antimicrobial potential of Saccharomyces boulardii extracts and fractions. J Appl Sci Res. 2012;8(8):4537-43.
13. Kelesidis T, Pothoulakis C. Efficacy and safety of the probiotic Saccharomyces boulardii for the prevention and therapy of gastrointestinal disorders. Ther Adv Gastroenterol. 2012 Mar;5(2):111-25. doi: 10.1177/1756283x11428502. [CROSSREF]
14. Fidanza M, Panigrahi P, Kollmann TR. Lactiplantibacillus plantarum–Nomad and Ideal Probiotic. Front Microbiol. 2021 Oct 6;12:712236. doi: 10.3389/fmicb.2021.712236. [CROSSREF]
15. Echegaray N, Yilmaz B, Sharma H, Kumar M, Pateiro M, Ozogul F, et al. A novel approach to Lactiplantibacillus plantarum: From probiotic properties to the omics insights. Microbiol Res. 2023 Mar;268:127289. doi: 10.1016/j.micres.2022.127289. [CROSSREF]
16. Murray CJL, Ikuta KS, Sharara F, Swetschinski L, Robles Aguilar G, Gray A, et al. Global burden of bacterial antimicrobial resistance in 2019: a systematic analysis. The Lancet. 2022 Feb;399(10325):629-55. doi: 10.1016/S0140- 6736(21)02724-0. [CROSSREF]
17. Veinović G. Uticaj uslova kultivisanja na rast, razmnožavanje, preživljavanje i morfološke odlike vrsta Borrelia afzelii, Borrelia garinii i Borrelia burgdorferi sensu stricto. Farmaceutski fakultet, Univerzitet u Beogradu; 2013.
18. Veinović G, Cerar T, Strle F, Lotrič-Furlan S, Maraspin V, Cimperman J, et al. In vitro susceptibility of European human Borrelia burgdorferi sensu stricto strains to antimicrobial agents. Int J Antimicrob Agents. 2013 Mar;41(3):288- 91. doi: 10.1016/j.ijantimicag.2012.11.016. [CROSSREF]
19. De Carvalho BT, Subotić A, Vandecruys P, Deleu S, Vermeire S, Thevelein JM. Enhancing probiotic impact: engineering Saccharomyces boulardii for optimal acetic acid production and gastric passage tolerance. Nygård Y, editor. Appl Environ Microbiol. 2024 Jun 18;90(6):e00325-24. doi: doi.org/10.1128/ aem.00325-24. [CROSSREF]
20. Rajkowska K, Kunicka-Styczyńska A. Probiotic activity of Saccharomyces cerevisiae var. boulardii against human pathogens [master’s thesis]. Zagreb: University of Zagreb, Faculty of Food Technology and Biotechnology; 2012.
21. De Simone N, Rocchetti MT, La Gatta B, Spano G, Drider D, Capozzi V, et al. Antimicrobial Properties, Functional Characterisation and Application of Fructobacillus fructosus and Lactiplantibacillus plantarum Isolated from Artisanal Honey. Probiotics Antimicrob Proteins. 2023 Oct;15(5):1406-23. doi: 10.1007/s12602-022-09988-4. [CROSSREF]
22. Chae M, Kim BJ, Na J, Kim SY, Lee JO, Kim Y jin, et al. Antimicrobial activity of Lactiplantibacillus plantarum APsulloc 331261 and APsulloc 331266 against pathogenic skin microbiota. Front Biosci-Elite. 2021 Dec 20;13(2):237. doi: 10.52586/e881. [CROSSREF]
23. Selegård R, Musa A, Nyström P, Aili D, Bengtsson T, Khalaf H. Plantaricins Markedly Enhance the Effects of Traditional Antibiotics Against Staphylococcus Epidermidis. Future Microbiol. 2019 Feb;14(3):195-205. doi: 10.2217/fmb2018-0285. [CROSSREF]
24. Surve S, Shinde DB, Kulkarni R. Isolation, characterization and comparative genomics of potentially probiotic Lactiplantibacillus plantarum strains from Indian foods. Sci Rep. 2022;12:1940. doi: 10.1038/s41598-022-05850-3. [CROSSREF]
25. Ružić-Sabljić E, Maraspin V, Stupica D, Rojko T, Bogovič P, Strle F, et al. Comparison of MKP and BSK-H media for the cultivation and isolation of Borrelia burgdorferi sensu lato. Stevenson B, editor. PLOS ONE. 2017 Feb 7;12(2):e0171622. doi: 10.1371/journal.pone.0171622. [CROSSREF]
26. Schwameis M, Kündig T, Huber G, Von Bidder L, Meinel L, Weisser R, et al. Topical azithromycin for the prevention of Lyme borreliosis: a randomised, placebo-controlled, phase 3 efficacy trial. Lancet Infect Dis. 2017 Mar;17(3):322- 9. doi: 10.1016/s1473-3099(16)30529-1. [CROSSREF]
27. Piesman J, Hojgaard A, Ullmann AJ, Dolan MC. Efficacy of an Experimental Azithromycin Cream for Prophylaxis of Tick-Transmitted Lyme Disease Spirochete Infection in a Murine Model. Antimicrob Agents Chemother. 2014 Jan;58(1):348-51. doi: 10.1128/aac.01932-13. [CROSSREF]
- Table 1. Range and median values of minimum inhibitory concentrations (MIC, %) of supernatants from Saccharomyces boulardii, Lactiplantibacillus plantarum, and their mixtures against Borrelia afzelii
- Table 2. Concentrations (%) and median values (%) of Saccharomyces boulardii, Lactiplantibacillus plantarum, and their mixed supernatants that exhibited a stimulatory effect on the growth and motility of Borrelia afzelii